Monday, November 11, 2019

Study: Security, facilities alleviate loneliness in over-65s

neighborhood
Credit: CC0 Public Domain
Living in a friendly, secure neighborhood is one of the key ways to keep loneliness and isolation at bay in older age, according to a study of over-65s living on the Kāpiti Coast.
11 nov 2019--And aspects of neighborhood design, like the provision of footpaths and lighting, and facilities such as transport, libraries, shops and services can also have an effect on the wellbeing of the elderly.
The Health in Ageing Research Team (HART) at Massey University's School of Psychology has just released the findings of a study called Social Connections carried out on behalf of Age Concern Kapiti and the Kāpiti Coast District Council.
Lead researcher Professor Christine Stephens says three quarters of the 919 respondents reported no loneliness, while a fifth reported moderate or high levels of loneliness. However, a more nuanced measure of loneliness revealed that nearly half of those who took part in the study (including Ōtaki, Waikanae, Paraparaumu, Paekakariki and Raumati) experience feelings of loneliness.
"Although the Kāpiti Coast has long been a favorite retirement venue, the levels of loneliness reported by older residents are similar to those found in other surveys across New Zealand," Professor Stephens says.
Marital status, health, restricted social networks, housing satisfaction, neighborhood accessibility, neighborhood security and neighborhood social cohesion contributed most strongly to differences in loneliness in this sample.
But the strongest associations with loneliness were related to housing and neighborhood perceptions. "Reports of higher satisfaction with housing, and sense of neighborhood security, accessibility, and social cohesion (trust in neighbors) were all related to less loneliness," the report authors say. In terms of the aspects of social life that can be changed to prevent or alleviate loneliness, being part of a positive, cohesive neighborhood mattered more than a person's group memberships and social activities, the study found.
Professor Stephens says that programs to prevent loneliness among older people generally focus on individual interventions, such as visitor programs or friendship groups. "These findings point to the importance of the neighborhood environment and have important implications for local and central government policy around housing and housing developments," she says. This includes aspects of neighborhood design like the provision of footpaths and lighting, and facilities such as transport, libraries, shops and services.
The report also emphasizes that people in low socio-economic settings are more likely to live in less well-serviced neighborhoods and these inequalities should be taken into account.
Different kinds of loneliness
Researchers used two established measures of loneliness. The first—the UCLA Loneliness Scale –showed 76.9 percent of respondents reported no loneliness, while 21.4 percent reported moderate or high levels of loneliness. However, using the more nuanced De Jong Gierveld Loneliness Scale, which distinguishes between social loneliness (the lack of people and friends around you) and emotional loneliness (the lack of intimate relationships or confidantes), nearly half of respondents reported moderate to high levels of loneliness.
"When we examined emotional and social loneliness separately, we found a difference in the incidence of these aspects of loneliness. Almost 35 percent reported some social loneliness while only 14 percent reported some emotional loneliness. These different categories provide some indication of the different types of support that could be provided for those with different loneliness needs: either more socializing, or more intimate support," the report's authors say.
Ages ranged from 65 to 98 across the sample, but age was not related to loneliness and nor was gender. Participants were selected randomly from the electoral roll, and the survey did not distinguish between people living independently and those in retirement villages. The study was funded by the Massey University Research Fund.
Dermot Whelan, manager of Age Concern Kapiti, says the survey findings will help his organization to address issues related to loneliness. "We now have an indication of the extent of loneliness among older people in Kāpiti and the impact social isolation can have. It was very interesting for us that the strongest associations with loneliness were found among housing and neighborhood perceptions such as neighborhood security, accessibility and trust."
The HART team is planning further research in 2020 to learn more about the ways in which neighborhoods are associated with loneliness and social connections.


Older adults find greater well-being in smaller social networks, study finds

older men
Credit: CC0 Public Domain
Are younger adults who cultivate numerous connections with friends, families and acquaintances through online social networks any happier than older adults who have smaller circles of face-to-face relationships? The answer may be no, according to research published by the American Psychological Association. Quality social relationships boost well-being and may be as important to people under age 45 as they are to those over age 60.
11 nov 2019--"Stereotypes of aging tend to paint older adults in many cultures as sad and lonely," said Wändi Bruine de Bruin, Ph.D., of the University of Leeds and lead author of the study. "But the research shows that older adults' smaller networks didn't undermine social satisfaction and well-being. In fact, older adults tend to report better well-being than younger adults."
The research was published in the journal Psychology and Aging.
Bruine de Bruin and her co-authors analyzed data from two online surveys conducted by RAND Corp.'s American Life Panel, a nationally representative survey of adults recruited through a variety of approaches (e.g., random digital dialing and address-based sampling).
Study participants assessed the number of people from different social networks (e.g., friends, family, neighbors) and peripheral others (e.g., coworkers, school or childhood relations, people who provide a service) with whom they had "regular contact in the past six months." Contact included face-to-face, by phone or email or on the internet. Participants also rated feelings of well-being over the prior 30 days.
Researchers found older adults had smaller social networks than younger adults, but the number of close friends was unrelated to age. Younger adults had large social networks consisting of mostly peripheral others, perhaps because online social media networking sites have facilitated the maintenance of increasingly large and impersonal social networks, according to the authors.
Only the reported number of close friends was associated with social satisfaction and well-being across the adult life span. The relationship between the number of close friends and well-being held, even after accounting for the number of family members, neighbors and peripheral others, which was not additionally associated with well-being.
The relationship of the reported number of close friends with greater social satisfaction and well-being did not vary with age, suggesting the importance of close friendships across the life span. This is consistent with observed patterns among Facebook users who reported greater well-being if they perceived more actual friends on their online social networks, according to Bruine de Bruin.
Some policymakers seem to be increasingly interested in improving well-being in older adults by expanding their social networks to combat loneliness, according to Bruine de Bruin.
"Loneliness has less to do with the number of friends you have, and more to do with how you feel about your friends," she said. "It's often the younger adults who admit to having negative perceptions of their friends. Loneliness occurs in people of all ages. If you feel lonely, it may be more helpful to make a positive connection with a friend than to try and seek out new people to meet."

More information: Wändi Bruine de Bruin et al, Age differences in reported social networks and well-being., Psychology and Aging (2019). DOI: 10.1037/pag0000415
Journal information: Psychology and Aging 
Provided by American Psychological Association 

Common muscle relaxant causes severe confusion in patients with kidney disease


kidney
Credit: CC0 Public Domain
One in 25 patients with very low kidney function were admitted to hospital with severe confusion and other cognitive-related symptoms a few days after being prescribed a common muscle relaxant.
11 nov 2019--A new study from ICES Western, Western University and Lawson Health Research Institute has shown that patients with kidney dysfunction who were prescribed a high dose of the drug baclofen, were more likely to be admitted to hospital for disorientation and confusion, than those who weren't prescribed the drug. Their results are being published on November 9 in the high impact journal, JAMA and are being presented at the same time at the American Society of Nephrology meeting in Washington, D.C.
"When we looked at people with low kidney function (30 per cent or less) who received a high dose of baclofen from their prescriber, approximately one in 25 were being admitted to hospital with severe confusion, typically over the next few days, " said Dr. Amit Garg, Professor at Western's Schulich School of Medicine & Dentistry and Scientist at ICES and Lawson. "If you compare that to a group of people who had low kidney function who didn't get baclofen, that risk is less than one in 500, so it's quite a dramatic difference between the two groups."
The research was initiated because of observations that nephrologists were noting in clinic at London Health Sciences Centre.
Dr. Peter Blake, Professor at Schulich Medicine & Dentistry, Lawson scientist and coauthor on the study says this drug is commonly prescribed for muscle spasms and muscle pain, and is also prescribed off-label for alcoholism, gastro-esophageal reflex disease, and trigeminal neuralgia. He says it is widely prescribed because it has not previously been associated with serious side-effects.
More than eight million prescriptions for the drug were handed out in the United States in 2016, and despite numerous case reports linking baclofen with cognitive symptoms in patients with kidney disease, this is the first population-based clinical study to look at the association between the two.


"It came to my clinical attention dealing with patients with advanced kidney failure, that this drug that is generally thought to be relatively harmless, appeared to be the precipitant of severe confusion," said Dr. Blake. "These are patients who had previously been very oriented, and they were suddenly extremely confused and when you took a history, we understood that they had recently started this drug, baclofen."
Using ICES data, the research team looked at a group of approximately 16,000 people in Ontario with kidney disease who started a new dose of baclofen between 2007 and 2018. They divided the patients into two groups, a group that received a high dose, and a group that received a low dose of the drug and compared both to a group of almost 300,000 kidney disease patients who were not prescribed the drug at all.
About 20 per cent of older adults live with kidney function of less than 60 per cent. The research team found that 1.11 per cent of such patients (108/9707) who started a high dose of the drug baclofen were admitted to hospital with cognitive-related symptoms, versus 0.42 per cent (26/6235) with the low dose. They found that the group most at risk had the lowest kidney function, 3.78 per cent of patients with kidney function less than 30 per cent were hospitalized with these symptoms after starting a high dose of baclofen (26/687).
"We found that in current practice most patients are getting a similar dose of baclofen no matter what the level their kidney function is," said Dr. Garg who is concerned about this discrepancy in dosing because prescribing guidelines already suggest a lower dose for patients with kidney dysfunction that isn't being followed. "We also found that the risk for hospitalization for severe confusion was higher amongst patients who received doses that were higher versus doses that were lower."
The authors hope this study will better inform physicians and pharmacists about the use of baclofen for patients with kidney disease. "This study shows quite clearly the potential harm of this drug.
When a patient with low kidney function presents to the hospital with confusion, when their medication list is reviewed baclofen should be considered as a potential culprit. We're hoping regulatory agencies will now take a look at this and perhaps add a new black box warning for baclofen. With this new information prescribers should reconsider risk-benefit, and should be quite cautious before they prescribe this drug. When they believe the  is indicated, a low dose should be considered, and patients and their families should be warned about what to look out for in terms of side effects."
The authors also say patients should not stop their prescription medications without talking to their doctor.

More information: Flory T. Muanda et al, Association of Baclofen With Encephalopathy in Patients With Chronic Kidney Disease, JAMA (2019). DOI: 10.1001/jama.2019.17725
Journal information: Journal of the American Medical Association 
Provided by University of Western Ontario

Where does Parkinson's disease start: In the brain, gut, or both?

Where does Parkinson's disease start? In the brain or gut? Or both?
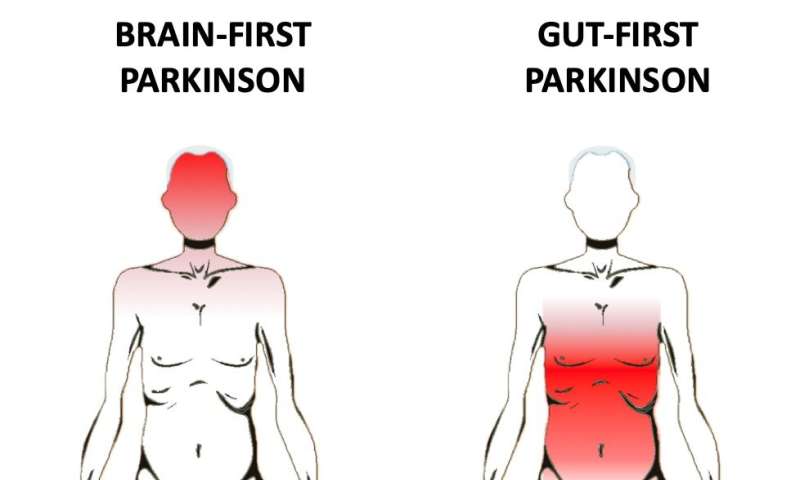
Leading experts in Parkinson's disease explore the hypothesis that Parkinson's disease can be divided into two subtypes: brain-first, and gut-first. Credit: Lundbeck Foundation.
Does Parkinson's disease (PD) start in the brain or the gut? In a new contribution published in the Journal of Parkinson's Disease, scientists hypothesize that PD can be divided into two subtypes: gut-first, originating in the peripheral nervous system (PNS) of the gut and spreading to the brain; and brain-first, originating in the brain, or entering the brain via the olfactory system, and spreading to the brainstem and peripheral nervous system.
11 nov 2019--Per Borghammer, MD, Ph.D., DMSc, Nuclear Medicine & PET, Aarhus University Hospital, Denmark, and Nathalie Van Den Berge, MSc, Ph.D., Department of Clinical Medicine, Aarhus University, Denmark, explore the origins of PD onset. They review the evidence that Lewy body disorders (LBD), including PD and dementia with Lewy bodies (DLB), comprise two distinct subtypes: (1) a gut-first phenotype in which marked damage to the peripheral autonomic nervous system precedes measurable damage to the brain itself, including the dopamine cells; and (2) a brain-first phenotype, in which marked damage to the brain precedes measurable damage to the peripheral autonomic nervous system.
"Evidence from autopsy studies of brains from PD patients has suggested that PD may start in the peripheral nervous system of the gut and nose. The pathology then spreads via the nerves into the brain. However, not all autopsy studies agree with this interpretation," explained Dr. Borghammer. "In some cases, the brains do not contain pathology at the important 'entry points' into the brain, such as the dorsal vagus nucleus at the bottom of the brainstem. The gut-first versus brain-first hypothesis posited in this review provides a scenario that can reconcile these discrepant findings from the neuropathological literature into one single coherent theory about the origins of PD."
"The discussion about the origins of PD is often framed as an 'either-or', i.e., either all PD cases start in the gut or all cases start in the brain," added Dr. Van Den Berge. "However, much of the evidence seems compatible with both these interpretations. Thus, we need to entertain the possibility that both scenarios are actually true."
The review summarizes existing evidence from imaging studies from humans and tissue studies from humans and animal models. The imaging and histology studies are generally compatible with the brain-first vs body-first hypothesis. If this hypothesis is correct, it suggests that PD is more complicated than originally thought. If the disease starts in the gut in only a fraction of patients, it is likely that interventions targeting the gut might only be effective for some PD patients, but not for individuals in which the disease starts in the brain itself.
"If the brain-first vs body-first hypothesis is correct, we need to intensify the research into understanding risk factors and triggering factors for these two subtypes," noted Dr. Van Den Berge.
"It is probable that these different types of PD need different treatment strategies," commented Dr. Borghammer. "It may be possible to prevent the 'gut-first' type of PD through interventions targeting the gut, such as probiotics, fecal transplants, and anti-inflammatory treatments. However, these strategies might not work with respect to treating and preventing the brain-first type. Thus, a personalized treatment strategy will be required, and we need to be able to identify these subtypes of PD in the individual patient."
PD is a slowly progressive disorder that affects movement, muscle control and balance. It is the second most common age-related neurodegenerative disorder affecting about three percent of the population by the age of 65 and up to five percent of individuals over 85 years of age. During the 20th century, PD was thought to be primarily a  disorder characterized mainly by loss of pigmented dopaminergic neurons residing in the substantia nigra, a basal ganglia structure located in the midbrain that plays an important role in reward and movement. More recently, it has become clear that PD is highly varied and probably consists of several subtypes.

More information: Per Borghammer et al, Brain-First versus Gut-First Parkinson's Disease: A Hypothesis, Journal of Parkinson's Disease (2019). DOI: 10.3233/JPD-191721
Journal information: Journal of Parkinson's Disease 
Provided by IOS Press 

Alzheimer's treatments: What's on the horizon?


alzheimers
Credit: CC0 Public Domain
Current Alzheimer's treatments temporarily improve symptoms of memory loss and problems with thinking and reasoning.
11 nov 2019--These Alzheimer's treatments boost performance of chemicals in the brain that carry information from one brain cell to another. However, these treatments don't stop the underlying decline and death of brain cells. As more cells die, Alzheimer's disease continues to progress.
Experts are cautiously hopeful about developing Alzheimer's treatments that can stop or significantly delay the progression of Alzheimer's. A growing understanding of how the disease disrupts the brain has led to potential Alzheimer's treatments that short-circuit basic disease processes.
Future Alzheimer's treatments may include a combination of medications, similar to how treatments for many cancers or HIV/AIDS include more than a single drug.
The following treatment options are among the strategies currently being studied.
Taking Aim At Plaques
Some of the new Alzheimer's treatments in development target microscopic clumps of the protein beta-amyloid (plaques). Plaques are a characteristic sign of Alzheimer's disease.
Strategies aimed at beta-amyloid include:
- Recruiting the immune system. Several drugs—known as monoclonal antibodies—may prevent beta-amyloid from clumping into plaques or remove beta-amyloid plaques that have formed and help the body clear the beta-amyloid from the brain. Monoclonal antibodies mimic the antibodies your body naturally produces as part of your immune system's response to foreign invaders or vaccines.
The monoclonal antibody solanezumab did not demonstrate any benefit for individuals with mild or moderate Alzheimer's disease. It's possible that solanezumab may be more effective when given earlier in the course of the disease. The drug seemed safe in recent studies, and solanezumab continues to be evaluated in the preclinical stage of the disease.
Aducanumab is another drug that has shown promise in preliminary studies. Study participants taking aducanumab had reduced amyloid plaque levels and a suggestion of possible delayed cognitive decline. More studies are underway for this treatment.
- Preventing destruction. Several years ago, researchers learned that beta-amyloid interacts with another protein called Fyn. When combined with beta-amyloid, Fyn is over-activated, which triggers a destruction of connections between nerve cells (synapses) in the brain. Studies are currently in progress for drugs that inhibit the Fyn protein. A drug initially developed as a possible cancer treatment—saracatinib—is now being tested in Alzheimer's disease. In mice, the drug turned off Fyn, which allowed synapses to start working again, and the animals experienced a reversal of some memory loss. Human trials for saracatinib as a possible Alzheimer's disease treatment are now underway.
- Production blockers. These therapies may reduce the amount of beta-amyloid formed in the brain. Research has shown that beta-amyloid is produced from a "parent protein" in two steps performed by different enzymes. Several experimental drugs aim to block the activity of these enzymes. They're known as beta- and gamma-secretase inhibitors. Recent studies showed that the beta-secretase inhibitor verubecestat did not slow down cognitive decline and was associated with several side effects in those with mild or moderate Alzheimer's.
Keeping Tau From Tangling
A vital brain cell transport system collapses when a protein called tau twists into microscopic fibers called tangles, which are another common brain abnormality of Alzheimer's. Researchers are looking at a way to prevent tau from forming tangles.
Tau aggregation inhibitors and tau vaccines are currently being studied in clinical trials.
Reducing Inflammation
Alzheimer's causes chronic, low-level brain cell inflammation. Researchers are studying ways to treat inflammatory processes at work in Alzheimer's disease. The drug sargramostim (Leukine) is currently in research. It's thought that the drug may stimulate the immune system to protect the brain from harmful proteins.
Researchers studied the diabetes drug pioglitazone (Actos) because it may lessen beta-amyloid and inflammation in the brain, but this trial was negative.
Researching insulin resistance
Researchers are studying the effects of insulin on the brain and brain cell function, and insulin changes in the brain that may be related to Alzheimer's. A trial testing an insulin nasal spray to determine whether it slows the progression of Alzheimer's was recently reported as negative.
Studying the heart-head connection
Growing evidence suggests that brain health is closely linked to heart and blood vessel health. The risk of developing Alzheimer's appears to increase as a result of many conditions that damage the heart or arteries. These include high blood pressure, heart disease, stroke, diabetes and high cholesterol.
A number of studies are exploring how best to build on this connection. Strategies under investigation include:
- Current drugs for heart disease risk factors. Researchers are investigating whether drugs such as blood pressure medications now used to treat vascular disease may also help people with Alzheimer's or reduce the risk of developing the disease.
- Drugs aimed at new targets. Additional projects are looking more closely at how the connection between heart disease and Alzheimer's works at the molecular level to find new drug targets.
- Lifestyle choices. Research suggests that lifestyle choices with known heart benefits, such as exercising on most days and eating a heart-healthy diet, may help prevent Alzheimer's disease or delay its onset.
Hormones
In one study, taking estrogen-based hormone therapy for at least a year during perimenopause or early menopause appeared to protect thinking and memory in women with a higher risk of Alzheimer's disease.
But further research has been conflicting, with some studies indicating that estrogen didn't offer any benefit. More research and a better understanding of the relationship between estrogen and cognitive function are needed before any recommendations can be made.
Speeding Treatment Development
Developing new medications is a slow and painstaking process. The pace can be especially frustrating for people with Alzheimer's and their families who are waiting for new treatment options.
To help accelerate discovery, the Coalition Against Major Diseases (CAMD), an alliance of pharmaceutical companies, nonprofit foundations and government advisers, has forged a first-of-its-kind partnership to share data from Alzheimer's clinical trials.
The CAMD has also collaborated with the Clinical Data Interchange Standards Consortium (CDISC) to create data standards. Researchers anticipate that these data standards and the sharing of data from more than 6,500 study participants will speed development of more-effective therapies.
©2019 Mayo Foundation for Medical Education and Research

Saffron effectively complements antidepressant medications

saffron
Credit: CC0 Public Domain
New research has shown that saffron may assist adults with depression when it is taken in conjunction with pharmaceutical antidepressants.
11 nov 2019--Murdoch University researchers Dr. Adrian Lopresti and Professor Peter Drummond, and UWA researcher Professor Sean Hood found greater reductions in depressive symptoms when adults with persistent depression, and currently taking a pharmaceutical antidepressant, complement their depression medication with saffron capsules.
Dr. Lopresti said that the trial was the largest of its kind to date and the first study looking at the effects of saffron as an add-on to pharmaceutical antidepressants. Previous research has only investigated the antidepressant effects of saffron as a stand-alone treatment.
"In our research, depressive symptoms decreased more in participants taking saffron compared with a placebo, with reductions of 41 and 21%, respectively on the clinician-rated scale," Dr. Lopresti said.
"In addition, improvements occurred in sleep quality, initiative and motivation, and interest and pleasure in activities."
Dr. Lopresti said that the study indicated that saffron could be used as a natural supplement given at the beginning of antidepressant treatment to increase its effectiveness and to possibly reduce potential adverse effects which are sometimes experienced when one is prescribed antidepressants.
"Saffron can be used at the outset in conjunction with antidepressants or it can be added to antidepressants if symptoms do not fully resolve," Dr. Lopresti said.
"At the moment, if pharmaceutical antidepressants aren't working the options are to increase the dose or to try a new antidepressant. This increases the likelihood of side effects. Now a new option is to take antidepressants and saffron together."
Background
  • Participants in the survey were randomly allocated to one of two trial groups, one taking a placebo and one taking a standardized saffron extract.
  • Participants were required to be physically healthy, aged 18–65 years and were taking a stable dose (at least eight weeks) of a single pharmaceutical antidepressant
  • More research needs to be undertaken to replicate these findings and to determine the longer-term benefits of saffron in treating symptoms of depression.
  • The findings do not mean the addition of saffron to cooking would necessarily promote antidepressant effects given the significant variance associated with the quality of saffron stigmas and the variability in extracts available on the market.
  • This study was funded by the manufacturer of the saffron extract, Pharmactive Biotech Products SL. However, Pharmactive Biotech Products was not involved in the design of the research, analysis of data, or in the writing of the report.

More information: Adrian L Lopresti et al. Efficacy of a standardised saffron extract (affron®) as an add-on to antidepressant medication for the treatment of persistent depressive symptoms in adults: A randomised, double-blind, placebo-controlled study, Journal of Psychopharmacology (2019). DOI: 10.1177/0269881119867703
Journal information: Journal of Psychopharmacology 
Provided by Murdoch University 

Sunday, November 03, 2019

High-tech 'Smart Care' apartment aims to improve health care for seniors

High-tech 'Smart Care' apartment aims to improve health care for seniors
UT Arlington Computer Science and Engineering Professors Manfred Huber and Gergely Zaruba test flooring with special sensors that will enable researchers to measure and evaluate changes in walking gaits and weight that might suggest illness or injury in residents. Credit: UT Arlington
University of Texas at Arlington nursing and engineering researchers will unveil a model "Smart Care" apartment next month that is infused with intelligent care technology designed to reduce risks encountered by older adults and those with disabilities who want to live independently in their own homes.
03 nov 2019--The federal Health Resources and Services Administration provided more than $600,000 in funding for the five-year project, which has been a collaborative effort involving premier faculty from the UT Arlington College of Nursing and Health Innovation and the College of Engineering. U.S. Rep Joe Barton, R-Arlington, advocated for the funding and said he is eager to see how the project - described as the first of its kind in Texas - will improve lives.
A grand opening event is scheduled at the Smart Care apartment at 10 a.m. May 7, 2015, at the Lakewood Village Senior Living Community, 5100 Randol Mill Road?in Fort Worth.
"UT Arlington is at the forefront of life-changing and innovative research in the area of Health and the Human Condition," Barton said. "Ultimately, Smart Care will positively impact senior citizens, people with disabilities, and injured veterans. It will also save money for people across the Dallas-Fort Worth area and nationwide by reducing the number of repeated trips to hospitals for some residents."
Christian Care Senior Living Communities generously contributed use of a 900-square foot, two-bedroom apartment at its Lakewood Village Senior Living Community in Fort Worth for the project.
"The entire Smart Care concept attracted us from the beginning because it just truly aligned with our mission to compassionately care for adults well into their golden years," said Phil Elmore, president and chief executive officer of Christian Care Senior Living Communities. "This has been a wonderful symbiotic partnership and we are proud to be a part of the work that UT Arlington is doing to expand horizons for senior citizens and people with physical challenges."
Carolyn Cason, co-principal investigator and professor of nursing, created the concept for establishing a Smart Care center at UT Arlington and a Smart Care apartment. She said the growing senior population and increasing number of Americans living with disabilities urgently demand research such as this.
"The technologies developed in the context of Smart Care will enable a significant improvement in preventive in-home health care for the aging, improve the efficiency and cost effectiveness of care by health care professionals, and improve the ability to directly involve family and friends into the care process."
Among other technologies, the Smart Care apartment includes:
  • Sensors underneath tiles on the floor that will allow researchers to measure and evaluate changes in walking gaits and weight that might suggest illness or injury;
  • A special camera embedded in a bathroom mirror that will tell researchers about day-to-day heart rate, facial expression, and skin color. Changes in expression and skin color can reveal aspects of the overall health status as well as about oxygen content of the blood;
  • Lift chair to help residents stand;
  • Smart appliances such as an LG microwave, range and refrigerator;
  • Connected exercise equipment, including a recumbent bike and interactive Kinect-based Tai Chi trainer;
  • Other systems that will detect whether medication is being properly managed or if the resident is not sleeping well or staying in bed too long.
Kathryn Daniel, an associate professor and director of the Adult-Gerontology Primary Care Nurse Practitioner Program in the College of Nursing and Health Innovation, serves as program manager for Smart Care. During a tour of the apartment in early April, she provided a behind-the-scenes look at the technology and explained how it will benefit clinicians, patients, families, and facility administrators. Watch a short video here.
The congressionally earmarked funding that Barton championed was used to purchase the high-tech kitchen appliances, a special toilet, automated beds, living room furniture, and other equipment in use at the Smart Care apartment, as well as at the center located in the UT Arlington Engineering Research Building.
The lab serves as mission control where researchers can unobtrusively monitor patients, interpret behavioral information and other data, and evaluate remote capabilities, health technologies and other protocols.
"Ultimately, the goal is to have these technologies in homes so that people could have warning signs if something is changing; you could also detect if something has already happened and there is a need to call for help," said Manfred Huber, co-principal investigator and professor in the UT Arlington Department of Computer Science and Engineering. "Again, the hope is that people can stay home much longer than they can currently." Watch a short video here.
Provided by University of Texas at Arlington 

High-salt diet promotes cognitive impairment through the Alzheimer-linked protein tau

salt
Credit: CC0 Public Domain
A high-salt diet may negatively affect cognitive function by causing a deficiency of the compound nitric oxide, which is vital for maintaining vascular health in the brain, according to a new study in mice from Weill Cornell Medicine researchers. When nitric oxide levels are too low, chemical changes to the protein tau occur in the brain, contributing to dementia.
03 nov 2019--In the study, published Oct. 23 in Nature, the investigators sought to understand the series of events that occur between salt consumption and poor cognition and concluded that lowering salt intake and maintaining healthy blood vessels in the brain may "stave off" dementia. Accumulation of tau deposits has been implicated in the development of Alzheimer's disease in humans.
"Our study proposes a new mechanism by which salt mediates cognitive impairment and also provides further evidence of a link between dietary habits and cognitive function," said lead study author Dr. Giuseppe Faraco, an assistant professor of research in neuroscience in the Feil Family Brain and Mind Research Institute at Weill Cornell Medicine.
The new study builds upon research published last year in Nature Neuroscience by Dr. Faraco and senior author Dr. Costantino Iadecola, director of the Feil Family Brain and Mind Research Institute and the Anne Parrish Titzell Professor of Neurology at Weill Cornell Medicine.
The 2018 study found that a high-salt diet caused dementia in mice. The rodents became unable to complete daily living tasks such as building their nests and had problems passing memory tests. The research team determined that the high-salt diet was causing cells in the small intestine to release the molecule interleukin-17 (IL-17), which promotes inflammation as part of the body's immune response.
IL-17 then entered the bloodstream and prevented the cells in the walls of blood vessels feeding the brain from producing nitric oxide. This compound works by relaxing and widening the blood vessels, allowing blood to flow. Conversely, a shortage of nitric oxide can restrict blood flow.
Based on these findings, Dr. Iadecola, Dr. Faraco and their colleagues theorized that salt likely caused dementia in mice because it contributed to restricted blood flow to the brain, essentially starving it. However, as they continued their research, they realized that the restricted blood flow in mice was not severe enough to prevent the brain from functioning properly.
"We thought maybe there was something else going on here,'" Dr. Iadecola said. In their new Nature study, the investigators found that decreased nitric oxide production in blood vessels affects the stability of tau proteins in neurons. Tau provides structure for the scaffolding of neurons. This scaffolding, also called the cytoskeleton, helps to transport materials and nutrients across neurons to support their function and health.
"Tau becoming unstable and coming off the cytoskeleton causes trouble," Dr. Iadecola said, adding that tau is not supposed to be free in the cell. Once tau detaches from the cytoskeleton, the protein can accumulate in the brain, causing cognitive problems. The researchers determined that healthy levels of nitric oxide keep tau in check. "It puts the brakes on activity caused by a series of enzymes that leads to tau disease pathology," he said.
To further explore the importance of tau in dementia, the researchers gave mice with a high-salt diet and restricted blood flow to the brain an antibody to promote tau stability. Despite restricted blood flow, researchers observed normal cognition in these mice. "This demonstrated that's what's really causing the dementia was tau and not lack of blood flow," Dr. Iadecola said.
Overall, this study highlights how vascular health is important to the brain. "As we demonstrated, there's more than one way that the blood vessels keep the brain healthy," Dr. Iadecola said.
Although research on salt intake and cognition in humans is needed, the current mouse study is a reminder for people to regulate salt consumption, Dr. Iadecola said. "And the stuff that is bad for us doesn't come from a saltshaker, it comes from processed food and restaurant food," he said. "We've got to keep salt in check. It can alter the  vessels of the  and do so in vicious way."
More information: Dietary salt promotes cognitive impairment through tau phosphorylation, Nature (2019). DOI: 10.1038/s41586-019-1688-z , https://www.nature.com/articles/s41586-019-1688-z
Journal information: Nature  , Nature Neuroscience 
Provided by Weill Cornell Medical College 

The first test to detect dysphagia in patients with cognitive problems

Scientists design first test to detect dysphagia in patients with cognitive problems
The UGR researchers who conducted this study. Credit: University of Granada
Researchers from the Mind, Brain and Behaviour Research Centre (CIMCYC) of the University of Granada (UGR) have designed a test to detect dysphagia, a disorder that prevents people from swallowing when eating. It affects 8 percent of the world's population.
03 nov 2019--Dysphagia is prevalent among older people in particular (30 percent to 40 percent of the elderly people admitted to hospitals or care homes) and patients with neurological or neurodegenerative disorders and diseases such as Alzheimer's, Parkinson's or multiple sclerosis, amyotrophic lateral sclerosis, cerebral palsy or strokes.
This difficulty in swallowing is due to the fact that the process of passing food or liquids from the mouth to the stomach requires more time and effort for these patients. Many die from aspiration pneumonia as a result of dysphagia. Yet dysphagia remains underdiagnosed because many of these patients suffer from cognitive disorders and cannot respond to functional evaluation processes.
To address this, the UGR researchers have designed and validated an early detection test for oropharyngeal dysphagia—called EdisfO—for patients with preserved cognitive status (that is, with no cognitive problems) that has also proven valid in patients with impaired cognitive status. This is the first time an assessment measure has been designed that successfully addresses this need.
The overarching aim of this research is to position the EdisfO as a widely-used tool that facilitates the diagnosis of possible dysphagia—a quick, safe, and effective test to screen for this disorder. It is currently being adapted and validated among the Turkish population, thanks to collaboration with Hacettepe University.
More information: Sandra Quirós et al. Design and Validation of the Oropharyngeal Dysphagia Screening Test for Patients and Professionals: A Preliminary Study, Dysphagia (2019). DOI: 10.1007/s00455-019-09999-4
Provided by University of Granada 

Wearable activity trackers a reliable tool for predicting death risk in older adults

elderly
Credit: CC0 Public Domain
A federally funded study by Johns Hopkins Medicine researchers shows that wearable accelerometers—mechanical sensors worn like a watch, belt or bracelet to track movement—are a more reliable measure of physical activity and better than patient surveys and other methods used by physicians at assessing five-year risk of death in older adults.
03 nov 2019--The research also added to evidence that an accurate and objective accounting of physical activity outperforms traditional predictors of mortality within five years, such as age, smoking, diabetes, alcohol use, or history of cancer or heart disease.
Based on these findings, the researchers say physicians could confidently use the devices' fitness profiles to help patients change unhealthy behaviors, increase physical activity and, potentially, extend healthy lifespans.
While their study is far from the first to report an association between physical activity and risk of death, the investigators say their findings, reported in the Oct. 15 issue of The Journal of Gerontology: Medical Sciences, is among the first to offer solid evidence that wearable activity trackers provide key predictors of mortality that outperform other measures.
"People can overestimate or underestimate on surveys how much and when they move, but wearable devices provide accurate data that cuts through the bias and guesswork," says Jacek Urbanek, Ph.D., assistant professor of medicine at the Johns Hopkins University School of Medicine and a member of the research team. "The technology is readily available and relatively inexpensive, so it seems feasible to be able to incorporate recommendations for its use into a physician's practice."
"We've been interested in studying physical activity and how accumulating it in spurts throughout the day could predict mortality because activity is a factor that can be changed, unlike age or genetics," says Ciprian Crainiceanu, Ph.D., professor of biostatistics at the Johns Hopkins Bloomberg School of Public Health, who is also a member of the research team.
For the new study, the researchers focused on the total amount of physical activity and times the participants were most active during the day.
First, using data from the National Health and Nutrition Examination Survey (NHANES) conducted by the U.S. Centers for Disease Control and Prevention (CDC), researchers looked at 33 predictors of five-year all-cause mortality, including 20 objective measures of physical activity, such as total activity, amount of time not moving or amount of time doing moderate to vigorous activity. In this way, they ranked physical activity and other factors, such as total cholesterol, smoking status, and having cancer or diabetes, to identify which ones best predict mortality within the following five years of the study population.
For their look at physical activity, the researchers used accelerometry data from nearly 3,000 adult Americans collected during the NHANES 2003-2004 and NHANES 2005-2006 surveys. Individual data came from responses to demographic, socioeconomic and health-related survey questions, along with information accessed from medical records and clinical laboratory test results. Participants were asked to wear an accelerometer device at the hip for seven consecutive days, removing it only when sleeping, showering or swimming.
The average age the study group was 65.9, and all participants were between 50 and 84 years old. While the gender proportion was nearly even—men made up 51%—a larger percentage of the men, 65%, died within five years of the study's follow up efforts.
After studying each individual variable associated with mortality—including education, sedentary time, and ethnicity—the researchers concluded that the total measure of physical activity accumulated during each day was the strongest predictor of five-year mortality, followed by age and moderate-to-vigorous activity. When comparing the data of a person who died within five years and a person who survived, researchers said they were able to correctly rank the mortality risk using accelerometers 30% more accurately than using information about smoking status and 40% better than using information about whether a person suffered a stroke or had cancer.
With a focus on fragmented activity, researchers also collected data for two-hour spans throughout the day in order to look at patterns in physical activities. Their analysis showed that physical activity—or lack thereof—between noon and 2 p.m. was the highest predictor of mortality risk, outperforming more commonly considered risk factors such as diabetes, cancer and alcohol consumption.
The researchers caution that their study wasn't designed to establish cause and effect, however, they did note that their data suggests that being more sedentary during the day is linked with higher mortality.
"The most surprising finding was that a simple summary of measures of activity derived from a hip-worn accelerometer over a week outperformed well-established mortality risk factors such as age, cancer, diabetes and smoking," says Ekaterina Smirnova, M.S., Ph.D., assistant professor of biostatistics at Virginia Commonwealth University and the lead author on the paper.
"While this study affirmed a link between physical activity and short-term mortality risk in an older population, the data don't guarantee that one's risk of mortality is going to be lower with more physical activity," noted Andrew Leroux, a Ph.D. candidate at Johns Hopkins and co-author of the study report. "However, our findings do indicate that an accurate measure of physical activity is a more reliable way for doctors and patients to assess physical activity and intervene to increase it as a potential way to improve health."
The researchers hope to use their data to help design clinical trials that could confirm the potential for physical activity to increase lifespan. One caveat to the study is that researchers aren't able to distinguish sedentary behavior from sleep or if someone has removed the device.

More information: Ekaterina Smirnova et al, The Predictive Performance of Objective Measures of Physical Activity Derived From Accelerometry Data for 5-Year All-Cause Mortality in Older Adults: National Health and Nutritional Examination Survey 2003–2006, The Journals of Gerontology: Series A (2019). DOI: 10.1093/gerona/glz193