Wednesday, February 24, 2021


Researcher offers lessons learned from a pre-pandemic study of telemedicine use

nursing home
Credit: Pixabay/CC0 Public Domain

With the onset of the COVID-19 pandemic, telemedicine has become a new norm for many routine and non-emergency medical needs. But there are lessons to be learned from telemedicine's use—or lack thereof—prior to the pandemic, and a new study from a UConn School of Social Work researcher offers insight for policymakers, administrators, and public health officials when considering the implementation of new services.

24 feb 2021--A qualitative researcher, lead author and licensed clinical social worker Kelsi Carolan was brought into the study—which was conducted in 2017 and 2018 and was recently published in the Journal of Medical Internet Research—to examine the adoption of a telemedicine program in a California independent senior living community.

"Initially, the study was purely looking at stats, seeing what the effects of this intervention would be, if any, on the unnecessary use of emergency transport—residents being transferred to the emergency department," Carolan says. "What my co-authors were seeing in the numbers was that it wasn't having much of an effect. The intervention didn't seem to be working."

Despite the fact that the program was being offered at no cost to residents, and despite a push from the community's administration to utilize the program for cases that were not medically urgent, telemedicine wasn't actually reducing the number of emergency room visits amongst residents in the community. The intervention uptake was low, and the researchers wanted to better understand why.

Carolan and her co-authors conducted separate focus groups with frontline, emergency-trained staff members and with residents from the community. The residents included both individuals who had previously used the telemedicine option as well as those who had not. Overall, the residents expressed a desire to avoid emergency room visits as much as possible—they disliked the long wait times, financial costs, and potential health risks of visiting the emergency room.

Some residents said the telemedicine option had helped avoid an unnecessary trip, while another said that their telemedicine experience actually reinforced the need to go to the emergency room despite the resident's initial hesitancy—an unexpected benefit that helped diagnose a serious heart condition and ultimately led to important treatment.

The perceptions and experiences of the residents, however, were often in direct contradiction to the opinions of the community's frontline staff, who reported in their focus groups that residents were reluctant to use the telemedicine option and did not directly request it. The staff felt that telemedicine ultimately just delayed an otherwise inevitable trip to the emergency room, seeing it as an obstacle to providing care to the community's residents and not a valuable tool.

"Staff were saying it's not appropriate for emergency care, and most folks need to go to the emergency room," says Carolan, who has previously conducted qualitative research looking at a community paramedicine intervention. "It really made me think about my previous work and how much of a culture shift it is to ask emergency-trained responders, like EMTs and paramedics, to start to think about preventing emergency transport. Especially EMTs, because it's just not what they're trained to do. It's really asking a profession to change its whole culture and training."

The researchers ultimately concluded that a key barrier to the telemedicine program's successful implementation was this resistance from staff, though Carolan says the COVID-19 pandemic may well have helped to change those cultural perspectives within the profession.

"I have faith that people who go into emergency care careers, like EMTs—they really want to help people," she says. "There's room for change if there is increased recognition among these frontline providers that sending people to the emergency room unnecessarily is not actually helping them and may actually cause harm. There might be a broader and more mainstream understanding now of the risks, at least related to COVID, of going into the emergency room when it's not necessary."

Carolan says that, in addition to not measuring the potential impact of the pandemic on attitudes, the study's sample was limited to the voluntary participation of residents at only one independent senior living community, and that the community's residents were of higher socioeconomic status, which may have meant they had access to additional resources that rendered telemedicine less appealing.

But she says that, as a clinician, there's a lot for practitioners—and policymakers—to learn from the study.

"One of the things about the study that I find really interesting is that it really highlights how there can be such a discrepancy sometimes between the preferences of the people that we're serving as providers and what the providers, in this case the EMT staff, believe is best," she says. "In addition, we really have to think carefully when we're trying to introduce these kinds of interventions—which is not even really specific to telemedicine -about the people who are on the ground actually trying to provide them. It's one thing for me to come in, as a researcher, or for these big intervention or demonstration projects to be put in place, but if the people on the ground who are actually in charge of delivering the intervention don't feel it is valuable or a good use of their time, then the whole thing may be destined to fail. For me, that encourages caution."

She says the study also highlights the importance of qualitative research in providing a more complete look at the effectiveness of policies and interventions.

"If we just looked at the quantitative data, the stats of the study, we would not really understand the full picture; we would just know that the telemedicine intervention wasn't really successful," Carolan says. "That's what it looks like with just the numbers. And I think what the study actually highlights is that it wasn't the full picture—the lack of uptake was related to the lack of provider buy-in."

She continues, "Often when people think about qualitative research, the thought is that it's not necessarily as relevant to policymaking as quantitative data because they think, 'Well, it's not representative. We can't extrapolate about the whole population from it.' But sometimes you're really losing an important part of the story when you aren't actually talking directly to people about what's going on."

More information: Kelsi Carolan et al, Use of Telemedicine for Emergency Triage in an Independent Senior Living Community: Mixed Methods Study, Journal of Medical Internet Research (2020). DOI: 10.2196/23014
Journal information: Journal of Medical Internet Research 


Study demonstrates the effectiveness of raloxifene in treating inflammatory processes associated with COVID-19

SARS-COV-2 , COVID-19
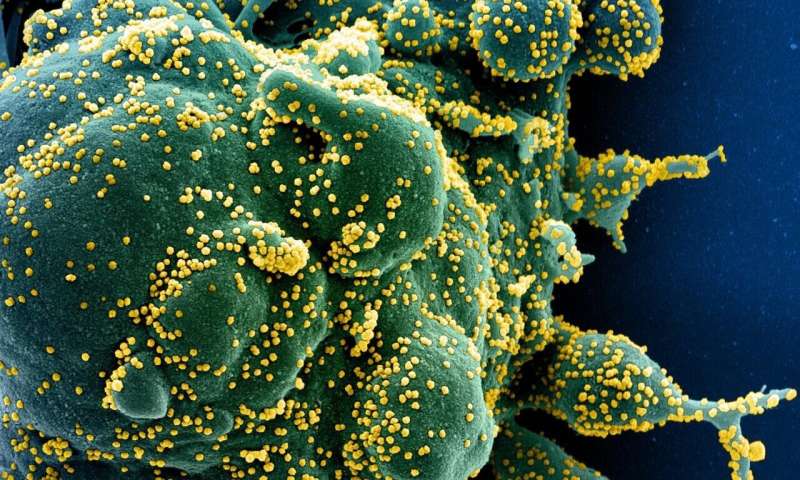
Colorized scanning electron micrograph of an apoptotic cell (green) heavily infected with SARS-COV-2 virus particles (yellow), isolated from a patient sample. Image captured at the NIAID Integrated Research Facility (IRF) in Fort Detrick, Maryland. Credit: NIH/NIAID

Researchers from the UPC's Molecular Biotechnology Centre show that a drug for osteoporosis called raloxifene may inhibit molecules involved in the inflammatory processes associated with COVID-19.

24 feb 2021--About 20% of COVID-19 patients have a severe clinical picture and require intensive care. These patients develop varying degrees of pneumonia that may evolve to more severe stages and cause organ dysfunction. Patients with severe symptoms exhibit elevated levels of proinflammatory molecules, a reaction known as cytokine storm. Recently, scientists have found that an inflammatory mediator known as bradykinin may trigger this inflammatory process that is observed in patients with severe COVID-19and that can be deadly.

In the fight against the disease, researchers are turning to drug repurposing to quickly provide a therapy by using already existing drugs. In this context, the researchers Juan Jesús Pérez and Patricia Gómez-Gutiérrez, from the Molecular Biotechnology Centre and linked to the Department of Chemical Engineering of the Universitat Politècnica de Catalunya · BarcelonaTech (UPC), have been looking for drugs to prevent bradykinin signaling. Using virtual drug screening, they have discovered that raloxifene, a drug used for osteoporosis and certain types of breast cancer, can act as a bradykinin inhibitor.

The study was conducted using computer-aided molecular design. The principal investigator, Juan Jesús Pérez, a professor at the Barcelona School of Industrial Engineering (ETSEIB), says, "We have performed drug screening using computer-aided drug design methods. After identifying the compound in silico, we sent a sample to an external laboratory for its in vitro characterisation, which corroborated its new pharmacological profile, and raloxifene has been shown to act as a partial agonist of bradykinin."

The conclusions of this research are set out in the article Discovery of a bradykinin B2 partial agonist profile of raloxifene in a drug repurposing campaign, which was published in the scientific journal International Journal of Molecular Sciences.

The increased availability of bradykinin in severe COVID-19 patients could be the trigger for cytokine storm. This hypothesis relies on the downregulation of angiotensin converting enzyme 2 (ACE2), the gateway for SARS-Cov-2 into cells, in such patients. This new perspective suggests that inhibition of bradykinin signaling may be a suitable therapy to prevent cytokine storm and its consequences.

Currently, icatibant is the only bradykinin antagonist approved as a therapeutic agent for the treatment of hereditary angioedema and it is now undergoing a clinical trial to assess its benefits for the treatment of COVID-19 patients. In fact, preliminary results from a limited study suggest that inhibition of bradykinin signaling is associated with decreased oxygen requirements in COVID-19 patients.

Raloxifene undergoing clinical trial as an antiviral agent

The result of the study by UPC researchers supports other studies suggesting the suitability of raloxifene in COVID-19 patients, based on its capacity to inhibit another inflammation signaling pathway, and also for being a prospective antiviral agent against severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2).

In the framework of a European project, the Exscalate4CoV consortium of supercomputing centers, including the Barcelona Supercomputing Center–Centro Nacional de Supercomputación (BSC-CNS), identified raloxifene, aimed at another therapeutic target, as an antiviral agent against SARS-CoV-2 in June 2020, also by using virtual screening techniques. Clinical trials are now underway in Italy to test its effectiveness in patients with mild symptoms.

Juan Jesús Pérez says, "The good results of the lines of research on raloxifene suggest that it is a good candidate drug against COVID-19."The researcher explains that "drug repurposing has long been used to discover new therapeutic uses for existing drugs, because it increases the chances that the compound can be used. In addition, clinical trials will not take as long as for a new drug, because its toxicity has already been tested."


More information: Patricia Gomez-Gutierrez et al. Discovery of a Bradykinin B2 Partial Agonist Profile of Raloxifene in a Drug Repurposing Campaign, International Journal of Molecular Sciences (2020). DOI: 10.3390/ijms22010257
Provided by Universitat Politècnica de Catalunya · BarcelonaTech (UPC)

Sunday, February 21, 2021


Machine learning can help doctors diagnose Parkinson's disease by looking at patients' movements

Parkinson's disease
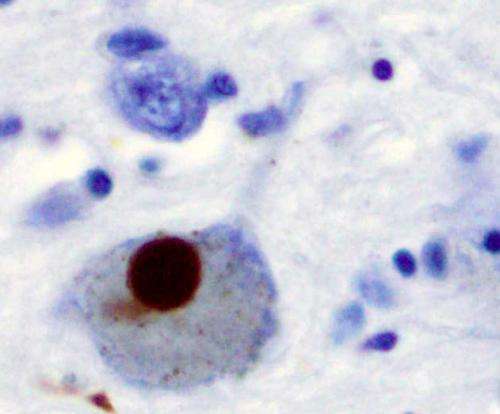
Immunohistochemistry for alpha-synuclein showing positive staining (brown) of an intraneural Lewy-body in the Substantia nigra in Parkinson's disease. Credit: Wikipedia

Scientists from Skoltech and A.I. Burnazyan Federal Medical and Biophysical Center have designed and developed a second opinion system based on AI-assisted video analysis that can help medical professionals to objectively assess patients with Parkinson's disease (PD), even at an early stage. This approach can help avoid misdiagnosing this disease, distinguishing between its stages, adjusting therapy and recommending diagnosed patients for deep brain stimulation surgery. The paper was published in IEEE Sensors Journal.

21 feb 2021--A growing number of people with neurodegenerative diseases, due to population aging, will mean that in the coming decades, humanity might face a bona fide Parkinson's disease pandemic. PD, currently the fastest growing neurodegenerative disease, affects the patients' quality of life quite severely and needs to be diagnosed as accurately and as early as possible. The challenge there is to distinguish between Parkinson's and other diseases with similar motor symptoms, for instance, essential tremor. So far, PD has no single biomarker that could be used to diagnose it consistently, and doctors have to rely on their observations, which often lead to wrong diagnoses revealed in pathological examinations.

Assistant Professor Andrey Somov and his colleagues built a so-called second opinion system that uses machine-learning algorithms to analyze video recordings of patients performing specific motor tasks. In a small pilot study, this system showed a very high level of performance in detecting potential cases of PD and distinguishing it from essential tremor.

The system uses video recordings, making the diagnostic process fast, unobtrusive and comfortable for the patients. The team designed a set of 15 common exercises such as walking, sitting down on chair, standing up, folding a towel, filling a glass with water, and touching one's nose with one's index finger. These were general and finer movements, no movement at all (to assess tremor at rest) and some activities that clinicians use to evaluate the tremor.

"The exercises were designed under the supervision of neurologists and came from several different sources, including scales that are used for monitoring Parkinson's disease and previous research done in this area. Each exercise had a target symptom that it could reveal," Ekaterina Kovalenko, Skoltech Ph.D. student and a coauthor of the paper, explained.

In the pilot study, 83 patients with or without neurodegenerative diseases were recorded performing these tasks. The videos were then processed using a piece of software that places keypoints onto the human body corresponding to joints and other parts of the body, creating simplified models of moving subjects. Those were analyzed using machine learning techniques.

The team says that the use of video and machine learning introduces a certain degree of objectiveness into the diagnostic process, allowing researchers and doctors to detect very specific features of the disease and its stages which are not visible to the naked eye.

"Our preliminary results show potential in improving diagnosis with the help of video analysis. Our goal is to provide a second opinion for doctors and clinicians, not to replace them. A video-based method perhaps is the most convenient for patients, as it is the most versatile and noninvasive when compared to various sensors and testing," the authors write in their paper.

"Machine learning and computer vision methods we used in this research are already well established in a number of medical applications; they can be trusted, and the diagnostic exercises for Parkinson's disease have been in development by neurologists for some time. What is truly new about this study is our quantitative ranking of these exercises according to their contribution to a precise and specific final diagnosis. This could only be achieved in collaboration between doctors, mathematicians and engineers," Dmitry Dylov, Skoltech Associate Professor and coauthor of the study, said.

In earlier studies, Somov's team also used wearable sensors in a similar feasibility study that helped them detect the most informative exercises for machine learning-assisted diagnosis of Parkinson's.

"As part of the research process, we had the opportunity to closely interact with doctors and medical personnel, who shared their ideas and experience. It was fascinating observing how two seemingly different disciplines came together to help people. We also had the opportunity to monitor all parts of the research, from designing the methodology to data analysis and machine learning," Kovalenko said.

"This collaboration between doctors and scientists in data analysis allows for many important clinical nuances and details that help achieve the best results. We as doctors see great potential in this; apart from differential diagnosis, we need objective tools to assess motor fluctuation in patients with PD. These tools can provide a more personalized approach to therapy and help make decisions on neurosurgical interventions as well as assess the outcomes of surgery later," neurologist Ekaterina Bril, a coauthor of the paper, noted.

Andrey Somov said the team's next goal is to combine video analysis and sensor data in the task of detecting PD and diagnosing its stages—they expect that this will improve accuracy. "We also keep in mind the innovation aspects of our work—our team agrees that it does make sense to consider converting our research results into an intuitive software product. We believe our joint research efforts will have a positive effect for the patients with PD," he added.

More information: Ekaterina Kovalenko et al. Distinguishing Between Parkinson's Disease and Essential Tremor Through Video Analytics Using Machine Learning: a Pilot Study, IEEE Sensors Journal (2020). DOI: 10.1109/JSEN.2020.3035240
Provided by Skolkovo Institute of Science and Technology 


COVID-19 telemonitoring program helps reduce hospital admissions and ER visits

patient
Credit: Unsplash/CC0 Public Domain

The rapid upscaling of a telemonitoring program in which health care providers performed daily telemedicine check-ins on COVID-19 patients faced a unique set of challenges. How these were resolved, and early outcomes, are reported in the peer-reviewed journal Telemedicine and e-Health.

21 feb 2021--"Kaiser Permanente's Virtual Home Care Program (VHCP) was able to rapidly establish a telemedicine-based program for the management of COVID-19 positive patients in the DC and Baltimore Metro regions. Preliminary data suggest that such a program may be effective in keeping patients out of the hospital and/or emergency room," stated James Shaw, MD, Med-Atlantic Permanente Medical Group, and coauthors.

The researchers described three main challenges. The constant flow of providers into and out of the program. Challenges in the management of Spanish-speaking patients and the need for translators. The initial lack of an alert system in the pulse oximetry program to alert patients and providers when a patient registered a low oxygen reading.

"The COVID-19 pandemic has provided an opportunity for telemedicine and telehealth to grow exponentially. Kaiser's work in the DC Metro area is a testament to providers developing and implementing new ways in rapid fashion in order to maximize health care delivery," says Charles R. Doarn, MBA, Editor-in-Chief of the Journal and Research Professor and Director of the Master of Public Health Program, Department of Environmental and Public Health Sciences, University of Cincinnati, Ohio.


More information: James G. Shaw et al, A Novel Large Scale Integrated Telemonitoring Program for COVID-19, Telemedicine and e-Health (2021). DOI: 10.1089/tmj.2020.0384
Provided by Mary Ann Liebert, Inc 

Wednesday, February 17, 2021

5 things you need to know about the AstraZeneca vaccine

vaccine
Credit: Pixabay/CC0 Public Domain

The Therapeutic Goods Administration (TGA) yesterday announced it has provisionally approved AstraZeneca's COVID vaccine for use in Australia.

17 feb 2021--The approval applies to people over 18, including adults older than 65. The recommended interval between the two doses is 12 weeks, but the second dose can be administered a minimum of four weeks after the first.

We now have two vaccines provisionally approved, which is welcome news for Australia's vaccine rollout. Vaccinations with the Pfizer shot are set to begin next week, and we should see inoculation with the AstraZeneca  start some time in March.

Here are five things to know about the AstraZeneca vaccine.

1. Storage and distribution

The Oxford/AstraZeneca vaccine, also known as ChAdOx1 nCoV-19, or AZD1222, is a viral vector vaccine. Scientists used an adenovirus, originally derived from chimpanzees, and modified it with the aim of training the immune system to mount a strong response against SARS-CoV-2 (the virus that causes COVID-19).

One key characteristic of this vaccine is that it can be stored at 2-8℃ (so, in a normal fridge). This is distinct from some of the other COVID-19 vaccines—such as Pfizer's mRNA vaccine—which must be stored at ultra-cold temperatures. So the AstraZeneca vaccine can be widely distributed with relative ease.

Additionally, AstraZeneca has multiple supply chains. Around the world they have multiple manufacturing sites, partners from whom to source ingredients, and distributors who can deploy the vaccine. These partnerships will accelerate production and distribution.

At this stage, the AstraZeneca vaccine will be the only locally available vaccine manufactured in Australia. Biotechnology company CSL has been working to upgrade its facilities so it can produce the vaccine locally at scale. It expects up to two million doses will be available by the end of March.

2. Safety and efficacy in people over 65

Phase 2 human trials tested safety and immune responses of the AstraZeneca vaccine, including in people over 65. The vaccine was found to be safe, showing just some mild and moderate reactions, and it induced similar immune responses across age groups.

Although the subsequent phase 3 trials included much larger numbers of people, they didn't include as many older people as trials for some of the other vaccines. So researchers couldn't confidently assess efficacy in this group at the time. Studies are ongoing, and there's still some uncertainty about the vaccine's efficacy in older people.

There are no specific safety concerns (especially based on overseas data) and the vaccine induces good immune responses, which is a positive indicator it could be effective in the elderly population. Therefore, the TGA has ruled the vaccine should be administered to elderly people "on a case-by-case basis" where the benefits outweigh the possible risks.

The person, their family and medical professionals might make the decision not to vaccinate if, say, the person is very elderly and frail, or has multiple medical conditions.

3. Timing of doses

In initial studies, the vaccine's efficacy was 62% with two standard doses. However, there was some variability depending on the dosage and timing.

Since then, scientists have asked questions about the optimal dose and interval. A preprint manuscript in The Lancet shows the vaccine demonstrated 82.4% efficacy after two standard doses three months apart. The efficacy was lower if the doses were closer together: 54.9% if the interval was less than six weeks.

Although this data is yet to be peer-reviewed, it suggests the timing between doses is a key factor in this vaccine's efficacy. The TGA has reflected this in its advice.

But will a person be protected already after one immunization, while waiting for the second boosting jab? The preprint study shows the vaccine has 76% efficacy after a single dose, when assessed over the first 90 days after vaccination.

4. Protection against different strains

As viruses mutate and give rise to new variants, this can affect how well certain vaccines work against them.

We've seen this with the B.1.351 variant of SARS-CoV-2, originally identified in South Africa. Following a multi-center clinical trial in South Africa, researchers concluded two doses of the AstraZeneca vaccine had minimal efficacy in mild to moderate COVID-19 cases, specifically due to the B.1.351 variant.

There's still hope the vaccine will be effective against more severe cases of COVID-19. But South Africa has halted the rollout of the AstraZeneca vaccine for now.

The news is looking better for the UK strain, B.1.1.7. In a phase 2/3 clinical trial in the UK, researchers concluded the AstraZeneca vaccine had an efficacy against the B.1.1.7 variant similar to that of other variants—74.6% compared with 84%. It's important to note this study is also a preprint, so it hasn't yet received the same scrutiny as other published research.

Interestingly, both the UK and South African variants have the same mutation—the N501Y mutation—but the south African variant has an additional mutation, E484K. Research shows this mutation contributes to the virus evading antibodies from COVID-19 patients against SARS-CoV-2.

5. Can it reduce transmission as well as disease?

This question has been asked of all COVID-19 vaccines, and emerging data for the AstraZeneca vaccine is encouraging. The Lancet preprint we mentioned earlier has shown this vaccine may block transmission after a single dose.

The researchers derived this data by taking weekly nose swabs from both symptomatic and asymptomatic cases and testing for the presence of the virus. (If a person has virus in their nose and are breathing it out, they're more likely to infect someone else.) They observed a 67% fall in swabs positive for the virus after one immunization.

In a separate preprint, people who received the AstraZeneca vaccine (as opposed to the placebo) and were swab positive showed reduced periods of viral shedding, which could also have a positive impact on transmission of disease.

This data suggests the AstraZeneca vaccine also has potential to substantially affect virus transmission, by reducing the number of highly infectious people in a population.


Provided by The Conversation 

Tuesday, February 16, 2021

Global weekly COVID cases are falling, WHO says—but 'if we stop fighting it on any front, it will come roaring back'

Global weekly COVID cases are falling, WHO says — but 'if we stop fighting it on any front, it will come roaring back'

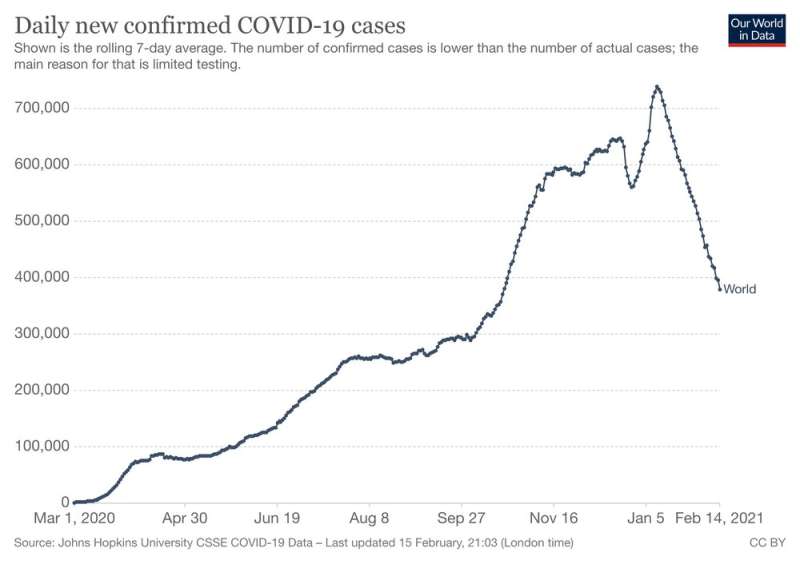
The number of reported global weekly COVID cases is falling and has dropped nearly 50% this year, the World Health Organization (WHO) said overnight. This incredibly encouraging news shows the power of public health measures—but we must remain vigilant. Letting our guard down now, when new variants are emerging, could easily reverse the trend.

16 feb 2021--According to a WHO press release: "Last week saw the lowest number of reported weekly cases since October", Tedros Adhanom Ghebreyesus, Director-General of the World Health Organization (WHO) told journalists at a regular press briefing in Geneva.

Noting a nearly 50% drop this year, he stressed that "how we respond to this trend" is what matters now.

While acknowledging that there is more reason for hope of bringing the pandemic under control, the WHO chief warned, "the fire is not out, but we have reduced its size".

"If we stop fighting it on any front, it will come roaring back".

This welcome news shows that when governments respond rapidly by putting in place public health measures, we reap the benefits even before widespread vaccine rollouts. That's a really important message now, and for when the next pandemic hits (and another one eventually will).

As good as this news is, though, we are still seeing infections in fairly large numbers worldwide. And, as we have regrettably seen in the past, subsequent waves of infection can easily emerge.

We also now have a series of variants to contend with. Even as begin to understand how the variants now circulating will affect the effectiveness of current vaccines, it's possible we could see yet another new variant emerge that would reverse the downward trend. This remains a real risk when there are still so many new infections worldwide and when so few countries have been able to start vaccinating.

Global weekly COVID cases are falling, WHO says — but 'if we stop fighting it on any front, it will come roaring back'

It's too early to see vaccine effect

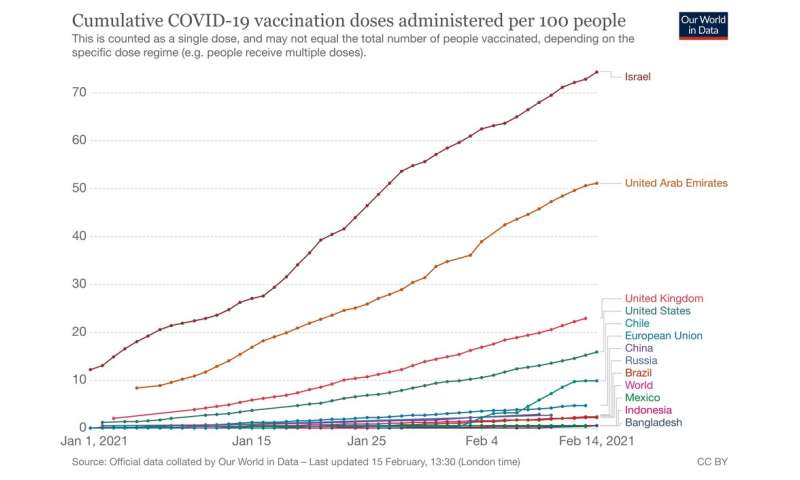
Some countries, such as Israel and the United Kingdom, have already vaccinated huge swathes of their population. That's a tremendous achievement and we will start to see the benefits in the coming months. But fundamentally, it's too early to see the effect of the vaccine rollout in widespread reduction of infection.

On the other hand, we have recently seen a much greater focus on public health measures in places such as Europe, the Middle East and the United States. These places have been significantly affected by COVID outbreaks and are dealing with third waves, as some are preparing for their fourth.

It's likely these public health measures—such as lockdowns, physical distancing, mask-wearing and increased hygiene measures—are what's driving the global downward trend. That shows the benefit when leaders do engage and bring their populations with them.

To keep that trend going in the right direction, we need high levels of public compliance with those public health measures and more equitable access to vaccines globally.

Unequal global access to vaccines is a major risk

Very few low-income countries have started a widespread vaccine rollout, and many are struggling to secure doses. Having unequal access globally to vaccines is obviously morally wrong and dangerous—but it also represents a great economic risk to high income countries like Australia.

Having high-income countries buying up all the stock of vaccines and leaving poorer nations with little recourse will prolong the pandemic. And that's bad news for the global economy, with estimates suggesting the pandemic will cost US$16 trillion dollars.

Even if Australia were able to maintain its success so far, having the pandemic run out of control in other countries means no travel, will continue to make it hard for Australians to return home, and could lead to shortages of products and materials from other countries. As the global financial crisis showed, economic strife in other parts of the world can have profound impact locally, even when Australia is doing relatively OK.

The risk this poses to lives and to the global economy is one reason the WHO has called for vaccine rollouts to begin in all countries in the first 100 days of 2021, and for health-care workers in lower- and middle-income countries to be protected first.

The WHO has issued a vaccine equity declaration calling for, among other things, world leaders to increase contributions to the UN-led vaccine equity initiative, COVAX, and to share doses with COVAX even as they roll out their own national campaigns.

We also clearly need to upscale vaccine research and manufacturing capacity around the world, which would also help us respond to the next pandemic, too.

There's still a lot of work to be done.

Relaxing too soon can undo our progress

As the WHO's Director-General said overnight, the fire is not out and "if we stop fighting it on any front, it will come roaring back".

That's why sticking to the fundamentals of infection control is so important. That means keeping up with the hand-washing and physical distancing. It means wearing a mask if you can't physically distance and complying with lockdowns and other public health orders. Yes, it's hard to maintain a high level of commitment, but the alternative is far worse.

When people start to hear that global case numbers are improving, there's a tendency to relax—and that's risky. Now is the time we need to work together to see this contained, and ideally suppressed.

We may never completely eradicate this virus. But if we stick with the public health measures, and vaccinate as many people as possible worldwide, we can keep the trend going in the right direction.


Provided by The Conversation 

Thursday, February 11, 2021

At least 50% of COVID-19 infections come from people who aren't showing symptoms: study

crowd
Credit: CC0 Public Domain

A new study out of the University of Chicago has found that during the initial wave of the COVID-19 outbreak in New York City, only 1 in 5 to 1 in 7 cases of the virus was symptomatic. The research team found that non-symptomatic cases substantially contribute to community transmission, making up at least 50% of the driving force of SARS-CoV-2 infection. The results were published on Feb. 10 in the Proceedings of the National Academy of Sciences.

11 feb 2021--When the COVID-19 epidemic arrived in the U.S., the investigators noticed that it was very difficult to estimate what proportion of people infected with SARS-CoV-2 would go on to develop symptoms, partially due to the initial challenges with testing capacity.

"Without testing capacity data, it's very difficult to estimate the difference between cases that were unreported due to a lack of testing and cases that were actually asymptomatic," said first author Rahul Subramanian, a Ph.D. student of epidemiology at UChicago. "We wanted to disentangle those two things, and since New York City was one of the first cities to report the daily  of tests completed, we were able to use those numbers to estimate how many COVID-19 cases were symptomatic."

While there are a number of existing models that use epidemiological data to estimate undetected case numbers and transmission rates, this is the first peer-reviewed model to incorporate data about daily testing capacity and changes in testing rates over time to provide a more accurate picture of what proportion of SARS-CoV-2 infections are symptomatic in a large U.S. city.

"Incorporating these data into the model showed that the proportion of individuals who are symptomatic for COVID-19 is somewhere between 13% and 18%," said senior author Mercedes Pascual, Ph.D., the Louis Block Professor of Ecology and Evolution at UChicago. "And regardless of uncertainty in all other parameters, we can tell that more that 50% of the transmission happening in the community is from people without symptoms ¬— those who are asymptomatic and pre-symptomatic."

While this data analysis does not indicate how infectious asymptomatic individuals are, nor account for the new variants of the virus currently spreading in the U.S., the model provides additional support for the importance of following public health guidelines to reduce community transmission of the virus, whether individuals show symptoms.

"Even if asymptomatic people aren't transmitting the virus at high rates, they constitute something like 80% of all infections," said co-author Qixin He, now an assistant professor at Perdue University. "This proportion is quite surprising. It's crucial that everyone—including individuals who don't show symptoms—adhere to public health guidelines, such as mask wearing and social distancing, and that mass testing is made easily accessible to all."

The investigators say that these results also demonstrate that public health agencies need to make their testing protocols and numbers publicly available to allow these data to be incorporated into existing transmission models.

"Making this information available is as important as reporting the number of cases," said Pascual. "Otherwise, we have a discrepancy between the number and type of cases that are reported over time and the underlying transmission dynamics. These data are critical for epidemiological modeling."


More information: Rahul Subramanian et al, Quantifying asymptomatic infection and transmission of COVID-19 in New York City using observed cases, serology, and testing capacity, PNAS March 2, 2021 118 (9) e2019716118; doi.org/10.1073/pnas.2019716118
Provided by University of Chicago Medical Center 

Monday, February 08, 2021


WHO warns against dismissing AstraZeneca vaccine after setbacks

covid
Credit: Unsplash/CC0 Public Domain

The World Health Organization and its Covax partners cautioned Monday against dismissing AstraZeneca's COVID vaccine after several setbacks, insisting it remained an important, life-saving tool.

08 feb 2021--The AstraZeneca vaccine is currently a vital part of Covax, which was set up to procure COVID-19 vaccines and ensure their equitable distribution around the world.

It accounts for almost all of the 337.2 million vaccine doses Covax is preparing to begin shipping to some 145 countries during the first half of the year, once it receives WHO authorisation, which is expected next week.

But the vaccine has run into several setbacks.

"It is vastly too early to be dismissing this vaccine," said Richard Hatchett, who heads the Coalition for Epidemic Preparedness Innovations (CEPI), which co-leads the Covax vaccine facility with the WHO and Gavi.

"It is absolutely crucial to use the tools that we have as effectively as we possibly can," he said, speaking at the WHO's regular bi-weekly press briefing on the coronavirus pandemic.

Regulatory authorities in several European nations have refused to authorise the vaccine for use among the over-65s—by far the most vulnerable age group for serious COVID-19 disease—due to a lack of data proving its efficacy among older people.

And South Africa said Sunday it would suspend the start of its COVID-19 vaccinations with the AstraZeneca jab after a study showed the jab failed to prevent mild and moderate cases of the virus variant that has appeared in the country.

'Concerning news'

WHO chief Tedros Adhanom Ghebreyesus told reporters that the study's findings were "clearly concerning news."

But he stressed that there were "some important caveats", pointing in particular to the small size of the study with only 2,000 participants, urging more research.

Other WHO experts also pointed out that the interval used between the two doses of the vaccine in the study was just a month—far shorter than what has been deemed to be optimal to enhance its efficacy.

WHO's vaccines chief Kate O'Brien pointed to other studies showing the vaccine could have a "meaningful impact against severe disease", including with the B.1.351 variant of the SARS-CoV-2 virus, first detected in South Africa.

She said the organisation's vaccine expert group, which met earlier Monday to discuss its recommendations on the use of the jab, had appeared optimistic about its prospects against the variant.

The 15-member Strategic Advisory Group of Experts on Immunization (SAGE) is due to render its verdict later this week.

However O'Brien said the experts had expressed "a very positive view on proceeding with the use of the vaccine including in settings where variants are circulating".

Gavi chief Seth Berkley agreed that current evidence indicated the jab "is an efficacious vaccine."

At the same time, he underscored the need to continue monitoring all the COVID vaccines, and possibly adapting them to better battle new variants "if found to be scientifically necessary."

The WHO's emergencies director Michael Ryan meanwhile said it was vital to use the tools available now to save lives.

"The primary job of vaccines right now is to reduce hospitalisations and deaths, and right now... they are working to do that," he said.

"We may need better vaccines to do more than just stop deaths and hospitalisations."

But "in emergency management you have got to do what you can do now," he added.

Sunday, February 07, 2021

Severely frail individuals with COVID-19 are three times more likely to die, study finds

Severely frail individuals with COVID-19 are three times more likely to die, study finds
Frailty. Credit: University of Birmingham

New research led by the University of Birmingham has revealed for the first time the extent to which frailty increases the risk of mortality in COVID-19 patients.

07 feb 2021--The clinical observational study, involving 5,711 patients with COVID-19 at 55 hospitals across 12 countries, found that very severely frail individuals with COVID-19 are three times more likely to die than those who were not frail, even taking into account their age. It also found that those with severe frailty who survived the virus were seven times more likely to go on to need increased care at home or in care homes.

The Geriatric Medicine Research Collaborative (GeMRC) - the group of experts behind the study—are now calling for improved global public health policy after their research showed that frailty, independently of older age, increases the risk of death from COVID-19.

Frailty is a state where the body becomes more vulnerable to the effects of illness. It is identified by clinicians using a holistic assessment that considers how much support the person needs from others in their daily living before becoming unwell—not just their medical problems, but the person as a whole. The risk of frailty increases as we get older, but it can develop at different ages.

Senior author Dr. Carly Welch, clinical research fellow in geriatric medicine at the University of Birmingham's Institute of Inflammation & Ageing, and Chair and Co-Founder of GeMRC, said: "It was identified very early in the pandemic that older age was a significant risk factor for a higher chance of death with Covid-19.

"However, not all older people are the same, we all age differently—some people can live well into their 90s without developing frailty, and it can develop even without the presence of other long-term conditions.

"Our findings are important as we have been able to demonstrate that not only older age but also frailty, independently from one another, increase the risk of death from COVID-19 and also a subsequent increased need in care for survivors."

Dr. Daisy Wilson, clinical research fellow at the University of Birmingham, added: "We now have evidence to show that those most at risk from COVID-19 are those who are older, or living with frailty, or have underlying health conditions."

GeMRC hopes the research findings will influence public health policy, including advice on shielding and recommendations for prioritisation on vaccination for those with frailty.

Dr. Mary Ni Lochlainn, of King's College London, added: "We hope that this research will help to enable increased understanding of frailty as occurring separately to age and that frailty can be considered alongside age in policies both in and outside of hospital.

"Increased understanding of frailty within the general public will enable improved communication between clinicians, patients, and their relatives or carers, and can be used in thinking about how we ensure that the right treatment is given for all patients in line with their wishes."

The research, published today (Feb 5th) in Age and Ageing and supported by the National Institute for Health Research (NIHR), is the largest international study of its kind to date.

The results also showed that delirium—a state of clouding of the mind and extremely prevalent in patients with COVID-19—is not itself independently associated with increased risk of mortality.

Meanwhile, the findings also showed an increased likelihood of transition to a higher level of care on discharge from hospital for those COVID-19 patients with increasing age, frailty, delirium, dementia, and mental health problems.

Further research is encouraged to understand what factors affect recovery of physical function and quality of life with COVID-19, and the inclusion of older adults with frailty in such research is paramount.


More information: Wilson et al (Feb, 2021). 'Age and frailty are independently associated with increased COVID-19 mortality and increased care needs in survivors: results of an international multi-centre study' Age And Ageing (2021). DOI: 10.1093/ageing/afab026

Saturday, February 06, 2021


AstraZeneca vaccine effective against UK variant: Oxford University

vaccine
Credit: Pixabay/CC0 Public Domain

Britain's Oxford University said on Friday its researchers behind the joint AstraZeneca Covid-19 vaccine had found it to be effective against the UK virus variant now dominant across the country.

06 feb 2021--The university, which developed the jab with the British-Swedish pharmaceutical firm, said an ongoing assessment of its effectiveness showed that it has "similar efficacy" to other coronavirus strains.

"Data from our trials... in the United Kingdom indicate that the vaccine not only protects against the original pandemic virus, but also protects against the novel variant," said Andrew Pollard, co-chief investigator on the Oxford vaccine trial.

The analysis, which relied on samples taken between October and mid-January, also indicated the jab reduces "duration of shedding and viral load", which may translate into reduced virus transmission, the university said.

The preliminary findings, which still need to be peer reviewed, are the first to report on the efficacy of the Oxford-AstraZeneca vaccine against new variants, it noted.

The more contagious British virus variant, which first emerged in southeast England in late September, has since become the most common strain detected in new UK infections, and spread to scores of other countries.

However, it is less clear how well the vaccines developed so far will work against several other variants that have emerged around the world, in particular a strain from South Africa that is causing concern.

Oxford said vaccine researchers are looking at ways to modify existing inoculations "quickly and simply" to protect against new variants.

"We have always expected that as the pandemic continues, new variants will begin to become dominant amongst the viruses that are circulating and that eventually a new version of the vaccine... would be required," said Sarah Gilbert, co-chief investigator of the Oxford trial.

"We are working with AstraZeneca to optimize the pipeline required for a strain change should one become necessary."


Friday, February 05, 2021

Neural roots and origins of alcoholism identified

Neural roots and origins of alcoholism identified
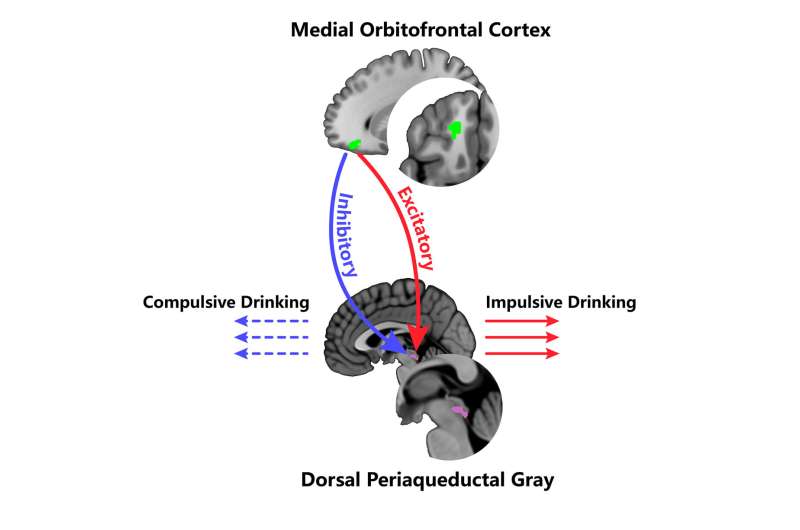
The medial orbitofrontal cortex – dorsal periaqueductal gray top-down regulations are linked to impulsive and compulsive drinking. Credit: University of Warwick

The physical origin of alcohol addiction has been located in a network of the human brain that regulates our response to danger, according to a team of British and Chinese researchers, co-led by the University of Warwick, the University of Cambridge, and Fudan University in Shanghai.

05 feb 2021--The medial orbitofrontal cortex (mOFC) at the front of the brain senses an unpleasant or emergency situation, and then sends this information to the dorsal periaqueductal gray (dPAG) at the brain's core, the latter area processing whether we need to escape the situation.

A person is at greater risk of developing alcohol use disorders when this information pathway is imbalanced in the following two ways:

  • Alcohol inhibits the dPAG (the area of the brain that processes adverse situations), so that the brain cannot respond to negative signals, or the need to escape from danger—leading a person to only feel the benefits of drinking alcohol, and not its harmful side effects. This is a possible cause of compulsive drinking.
  • A person with alcohol addiction will also generally have an over-excited dPAG, making them feel that they are in an adverse or unpleasant situation they wish to escape, and they will urgently turn to alcohol to do so. This is the cause of impulsive drinking.

Professor Jianfeng Feng, from the Department of Computer Science at the University of Warwick and who also teaches at Fudan University, says, "I was invited to comment on a previous study on mice for the similar purpose: to locate the possible origins of alcohol abuse. It is exciting that we can replicate these murine models in humans, and, of course, go a step further to identify a dual-pathway model that links alcohol abuse to a tendency to exhibit impulsive behavior."

Professor Trevor Robbins from the Department of Psychology at the University of Cambridge says, "It is remarkable that these neural systems in the mouse concerned with responding to threat and punishment have been shown to be relevant to our understanding of the factors leading to alcohol abuse in adolescents."

Dr. Tianye Jia from the Institute of Science and Technology for Brain-inspired Intelligence at Fudan University, also affiliated with King's College London, says, "We have found that the same neural top-down regulation could malfunction in two completely different ways, yet leading to similar alcohol abuse behavior."

Published in the journal Science Advances, the research is led by an international collaboration, co-led by Dr. Tianye Jia from Fudan University, Professor Jianfeng Feng from the University of Warwick and Fudan University, and Professor Trevor Robbins from the University of Cambridge and Fudan University.

The research team had noticed that previous rodent models showed that the mPFC and dPAG brain areas could underlie precursors of alcohol dependence.

They then analyzed MRI brain scans from the IMAGEN dataset—a group of 2000 individuals from the UK, Germany, France and Ireland who take part in scientific research to advance knowledge of how biological, psychological and environmental factors during adolescence may influence brain development and mental health.

The participants undertook task-based functional MRI scans, and when they did not receive rewards in the tasks (which produced negative feelings of punishment), regulation between the mOFC and dPAG was inhibited more highly in participants who had exhibited alcohol abuse.

Equally, in a resting state, participants who demonstrated a more overexcited regulation pathway between the mOFC and dPAG, (leading to feelings of needing urgently to escape a situation), also had increased levels of alcohol abuse.

Alcohol use disorder (AUD) is one of the most common and severe mental illnesses. According to a WHO report in 2018, more than 3 million deaths every year are related to alcohol use worldwide, and harmful alcohol use contributes to 5.1% of the global burden of disease. Understanding how alcohol addiction forms in the human brain could lead to more effective interventions to tackle the global problem of alcohol abuse.


More information: Tianye Jia et al. Neural network involving medial orbitofrontal cortex and dorsal periaqueductal gray regulation in human alcohol abuse, Science Advances (2021). DOI: 10.1126/sciadv.abd4074
Provided by University of Warwick